
Fractional Flow Reserve (FFR)
Does your coronary narrowing really need treating?
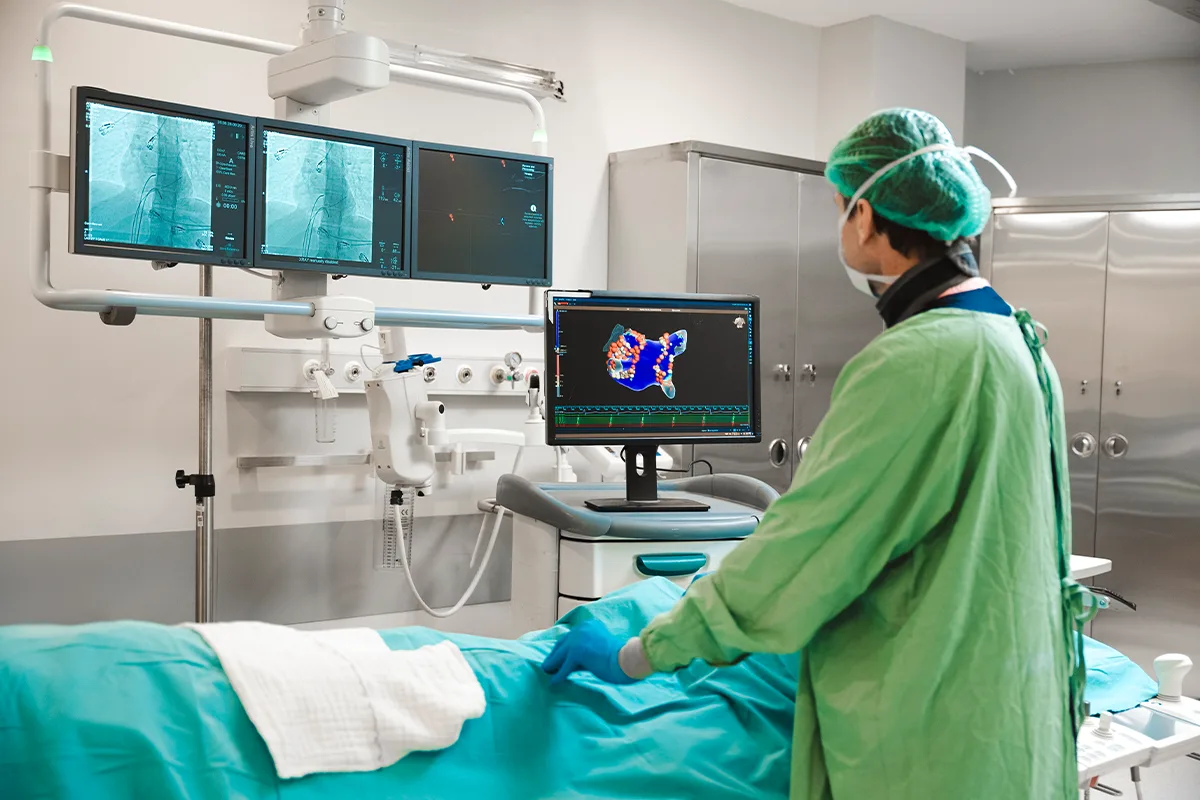
Not every narrowing seen on a coronary angiogram has to be treated with a stent. Fractional flow reserve (FFR) is a measurement that shows whether a particular narrowing is genuinely reducing the blood supply to the heart muscle. During the angiogram, a very fine pressure wire is passed along the artery and the pressure is measured before and beyond the narrowing. There is one aim: to treat the right artery, at the right time.
What Is FFR?
FFR compares the blood pressure in a coronary artery before and beyond a narrowing. The initials stand for fractional flow reserve.
The idea behind it is simple. In a healthy artery, blood travels from one end to the other with almost no loss of pressure. If a narrowing is restricting the flow, the pressure beyond it drops noticeably. The ratio between the two pressures gives a number, and that number shows what the narrowing actually means for the heart.
This makes FFR a functional assessment rather than an anatomical one. It measures what the narrowing does, not what it looks like.
Why Isn’t Every Narrowing Stented?
A coronary angiogram is an imaging test. It shows the outline of the artery in two dimensions, and the percentage of the narrowing is estimated from that picture.
Here is the difficulty: two narrowings that look the same to the eye can affect the blood supply very differently. The length of the narrowing, the diameter of the artery, the amount of muscle it feeds and the state of its side branches all change the answer.
It is hardest with intermediate narrowings — roughly between 40 and 70 per cent — where the picture alone does not settle the question. This is where the decision to stent is most often debated.
Stenting a narrowing that is not restricting flow does not add to the benefit of well-managed medical treatment. Every stent, on the other hand, brings its own follow-up and its own course of blood-thinning medication. This is where FFR earns its place: it helps avoid stents that are not needed, and makes sure that the narrowings which do need treating are treated.
How Is FFR Measured?
FFR is not a separate procedure. It is done in the same session as the coronary angiogram, through the same access point. You do not need to come back a second time.
Access. Under local anaesthetic, the artery is entered at the wrist (the radial route) or at the groin — the same access point already being used for the angiogram.
Passing the wire. A guide wire a little thicker than a human hair, with a pressure sensor at its tip, is passed beyond the narrowing.
Opening the artery up. A medicine called adenosine is given, which widens the artery as far as it will go for a short time. This state is called hyperaemia, and the measurement is only accurate while it lasts.
The measurement. The pressures before and beyond the narrowing are recorded at the same moment and the ratio is calculated.
The decision. The result appears on the screen straight away. If treatment is needed, the balloon and stent can follow in the same session.
What Will You Feel?
You will not feel the wire moving inside the artery. There are no pain-sensing nerve endings inside blood vessels.
While the adenosine is running, though, you are expected to feel something. There may be pressure in the chest, a flush of heat, tightness in the throat or a short spell of breathlessness. It is unpleasant, but the drug is short-acting: once it is stopped the feeling usually passes within seconds. Do tell the team if you are uncomfortable.
How Long Does It Take?
Assessing a single artery usually adds a few minutes to the angiogram. If more than one artery is measured, it takes correspondingly longer. The time you spend being observed afterwards is the same as it would be after an angiogram on its own.
What Should the FFR Value Be?
An FFR of 0.80 or below means the narrowing is restricting the blood supply to the heart muscle to a meaningful degree, and treatment is considered. Values above 0.80 show that the narrowing is not affecting the flow appreciably, and medical treatment is usually continued.
The closer the number is to 1.00, the more the artery is behaving as a normal one would.
There is a detail here that most sources leave out. Between 0.75 and 0.80 is a grey zone. In that range the decision is not made on the number alone. Your symptoms, which artery is involved, how much muscle it supplies and your other test results are weighed together.
In short, the FFR value is a tool for reaching the decision; it is not the decision.
What If the Result Says No Stent Is Needed?
This is what unsettles patients most. The thought that there is a narrowing and nobody is touching it causes worry.
If the measurement shows that the narrowing is not restricting flow, continuing with medication is the right approach. That does not mean nothing is being done. Treatment includes:
Cholesterol-lowering treatment and blood-thinning medication
Keeping blood pressure and blood sugar under control
Stopping smoking
Regular walking and a settled way of eating
Cardiology review at set intervals
To be straight about it: the narrowing does not disappear because it has been measured. If the risk factors are not brought under control, it can progress over time. So if your symptoms change, see your doctor without waiting.
Who Is FFR For?
It helps where the picture alone does not settle the decision. Common examples:
A single narrowing that looks intermediate on the angiogram
Narrowings in more than one artery, where it matters which of them is responsible
An exercise test or a perfusion scan that is inconclusive, or that disagrees with the angiogram
Choosing between a stent and bypass surgery
Assessing a narrowing around a stent placed earlier
When FFR Is Not the Right Test
FFR is not needed for every narrowing, and in some situations it is not suitable:
If the narrowing is very severe, or the artery is completely blocked, the decision is already clear and no measurement is needed. Completely blocked arteries are treated through CTO (chronic total occlusion) procedures.
During an ST-elevation heart attack, the artery causing it is not measured. It is treated without losing time.
Adenosine needs care in people with severe asthma, advanced chronic lung disease or certain rhythm disorders. Methods that do not require adenosine may be preferred for them.
Whether this is the right test for you is decided after your existing results and your symptoms have been considered together.
How Do FFR, iFR and IVUS Differ?
The three can look interchangeable, but they answer different questions.
FFR: a functional measurement based on pressure, taken with the artery widened by adenosine. Its question is whether the narrowing is restricting blood flow.
iFR (instantaneous wave-free ratio): also based on pressure, but it measures during one particular part of the heart cycle, so adenosine is not needed. It may be preferred where adenosine is unsuitable.
IVUS (intravascular ultrasound): not a measurement but an imaging method. An ultrasound probe inside the artery shows the make-up of the plaque, the diameter of the vessel and how a stent is sitting.
Put simply: FFR and iFR show what the artery is doing, IVUS shows what it looks like. In complex procedures they often complement one another and can be used together in the same session.
FFR in Antalya
Prof. Dr. Umuttan Doğan is a cardiologist working in interventional cardiology and complex coronary procedures. FFR is carried out in the catheter laboratory at Antalya American Hospital, in the same session as the coronary angiogram.
If you have already had an angiogram and were told the narrowing was borderline, you can be seen at the clinic in Konyaaltı with the images and results you already have. You will find his background and contact details on their own pages.
Frequently Asked Questions
Is FFR a separate procedure? Will I need a second angiogram?
No. FFR is done during the coronary angiogram, through the same access point. There is no separate appointment and no second procedure.
At what FFR value is a stent placed?
In general, values of 0.80 and below show that the narrowing is restricting blood flow, and treatment is considered. Between 0.75 and 0.80 is regarded as a grey zone, where the decision is reached by weighing your symptoms and your other findings together.
Will it hurt?
You will not feel the wire moving. When the adenosine is given there may be pressure in the chest, a flush of heat or a short spell of breathlessness. That comes from the drug and usually passes within seconds of stopping it.
No stent was placed — could my artery block later?
The measurement shows that the narrowing is not restricting blood flow today; the narrowing itself does not go away. If cholesterol, blood pressure, blood sugar and smoking are not kept under control, it can progress over time. That is why the medication and regular review matter.
Is FFR done for every patient?
No. Where the narrowing is very severe or the artery is completely blocked, the decision is already clear. During an ST-elevation heart attack the artery responsible is not measured. Adenosine needs care in people with severe asthma or advanced lung disease, and methods that do not require it can be considered for them.
The information on this page is for general guidance and does not replace a consultation. Decisions about diagnosis and treatment are made by your doctor after assessing your own situation.